

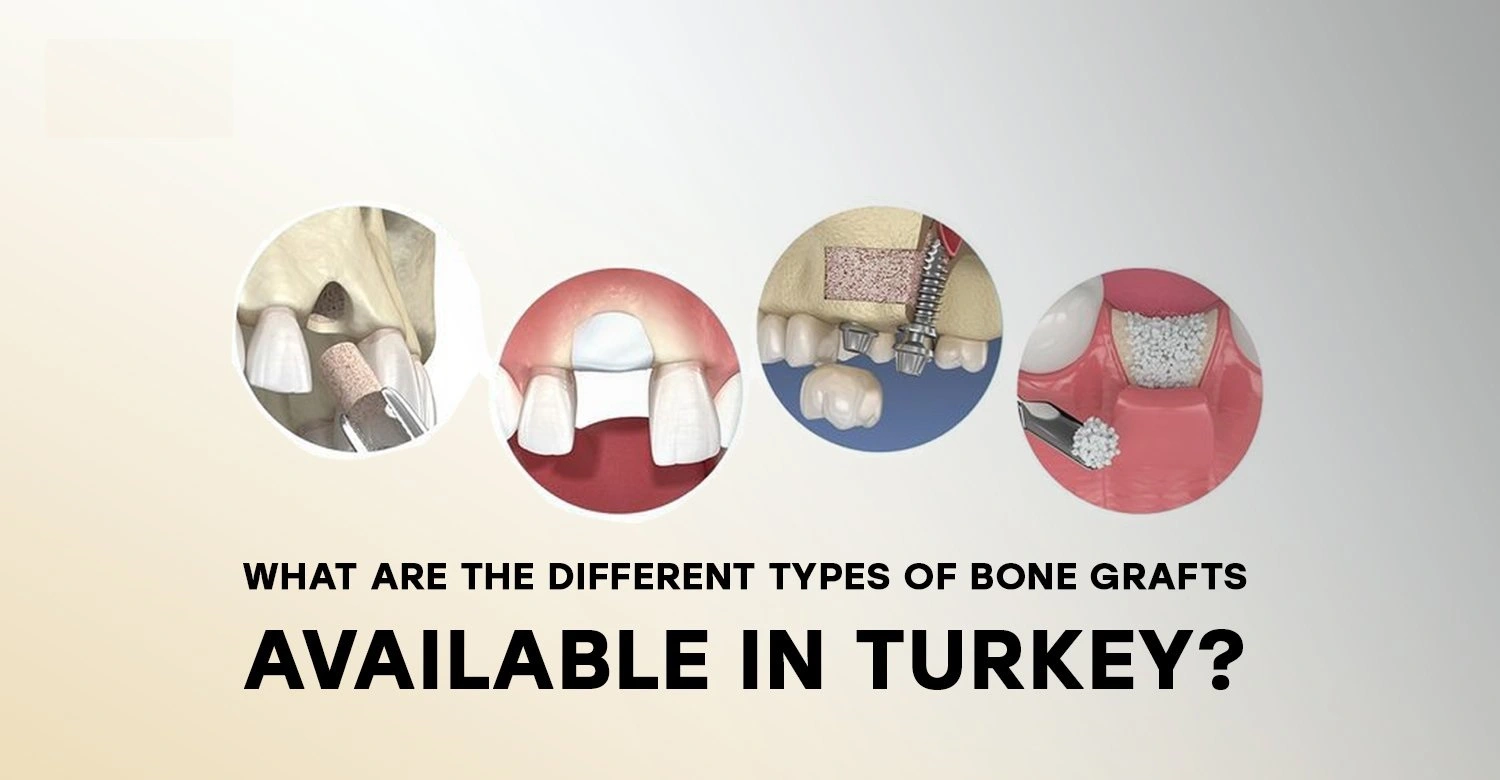
Jawbone resorption creates significant hurdles when planning permanent tooth replacement. When a natural tooth is extracted or lost to severe periodontal disease, the surrounding jawbone loses crucial mechanical stimulation. Over time, the body resorbs this inactive bone matrix, reducing available bone height and width. For patients seeking long-term stability through modern implant dentistry, adequate bone volume is non-negotiable. Placing a dental implant in insufficient bone risks nerve damage, sinus perforation, aesthetic failure, or complete fixture mobility. This clinical guide provides an honest evaluation when looking at bone grafting types compared, analyzing every material class, surgical application, success rate, and practical trade-off involved in jaw reconstruction.
Navigating various bone augmentation techniques requires understanding how biological tissue heals. Bone grafting is not simply filling a hole with material. Instead, it relies on biological mechanisms including osteogenesis, osteoconduction, and osteoinduction. Selecting the correct material depends on individual patient anatomy, budget, surgical site architecture, and healing tolerance. Below, we break down each primary grafting category with raw clinical transparency.

Autografts: Biological Excellence versus Dual Surgical Sites
Autogenous bone grafting involves harvesting living bone tissue directly from one part of the patient’s own body to rebuild the targeted jaw region. Common intraoral donor sites include the mandibular ramus or chin, while extensive reconstructive cases may utilize extraoral sites like the iliac crest. Because the graft originates from your own tissue, it contains living osteoblasts, growth factors, and active cellular scaffolding.
Biologically, autografts remain unrivaled because they provide osteogenesis, osteoinduction, and osteoconduction simultaneously. However, the clinical downside is significant: it requires a secondary donor site. This secondary surgical site introduces additional tissue trauma, increased post-operative pain, extended surgical time, and heightened risks of localized nerve paresthesia. For single-tooth implants, modern surgeons frequently favor off-the-shelf alternatives unless severe vertical defect reconstruction is mandatory.
Allografts: Human Donor Tissue without Secondary Invasiveness
Allografts utilize processed human donor bone tissue sourced through certified tissue banks. These materials undergo rigorous sterilization, demineralization, and freeze-drying processes to eliminate cellular antigens and pathogens, leaving behind an acellular matrix rich in minerals and structural collagen.
Available as Freeze-Dried Bone Allograft or Demineralized Freeze-Dried Bone Allograft, this material acts as an exceptional osteoconductive framework. The primary clinical advantage of allografts is eliminating donor-site morbidity. Patients undergo a single surgical site procedure, reducing surgical stress and recovery timelines. The trade-off is complete dependence on host cell invasion to remodel donor tissue. Healing times are slightly longer than autogenous tissue, and some patients feel hesitant regarding human donor origin.
Xenografts: Animal Derived Scaffolds for Volume Preservation
Xenografts are bone grafting materials derived from another species, most frequently bovine or porcine sources. Through high-temperature processing and chemical extraction, organic components are completely purged, leaving an inorganic hydroxyapatite matrix identical to human bone structure.
The primary clinical strength of a xenograft is its slow resorption rate. While autografts remodel rapidly into host bone, xenograft particles remain structural for years, acting as a stable space maintainer. This makes xenografts ideal for aesthetic zone procedures, socket preservation, and sinus lifts where structural volume maintenance over time is critical. The drawback is that xenograft particles rarely convert entirely into vital human bone; instead, they become encapsulated by host bone, functioning as a long-term microscopic scaffold.
Synthetic Bone Grafts: Engineered Alloplastic Alternatives
Alloplasts represent synthetic, lab-manufactured bone substitute materials engineered from calcium phosphate ceramics, tricalcium phosphate, hydroxyapatite, or bioactive glass formulations. Because they are completely synthetic, they eliminate any potential risk of cross-species disease transmission or donor tissue concerns.
Synthetic materials operate strictly through osteoconduction, serving as a temporary structural matrix for native bone growth. Advanced biphasic ceramic products offer controlled degradation rates, balancing graft resorption with new bone formation. While predictable for minor localized defects and routine socket fillings, synthetics lack biological signaling molecules or live cells. Consequently, they are less effective when used alone in massive multi-dimensional bone defects without mixing with biological concentrates.
Composite Bone Grafts: Strategic Material Blending
In contemporary implant surgery, clinicians rarely limit themselves to a single unmixed material. Composite grafting involves combining two or more graft types to harness the distinct benefits of each. A common clinical combination includes mixing autogenous bone scrapings with bovine xenograft particles.
In this hybrid approach, the autograft provides live bone cells and immediate growth factor release, while the xenograft offers long-term space maintenance and resists volume collapse during healing. By tailoring graft mixtures to specific defect architecture, oral surgeons achieve optimal healing speed alongside long-lasting structural volume stability.
Osteogenesis: Direct Living Bone Cell Formation
Understanding biological bone healing requires breaking down key physiological mechanisms. Osteogenesis refers to direct new bone formation by living, viable osteoblasts contained within the graft material. Only fresh autogenous graft tissue possesses true osteogenic capability, making it uniquely effective for rapid bone bridging in complex structural voids.
Osteoinduction: Chemical Stimulation of Host Stem Cells
Osteoinduction is the biological process where chemical signals recruit undifferentiated mesenchymal stem cells from the host site and trigger their transformation into bone-forming osteoblasts. Autografts and specific demineralized human allografts demonstrate true osteoinductive properties, accelerating early healing phases.
Osteoconduction: Passive Physical Scaffolding Architecture
Osteoconduction is the physical property where a porous graft matrix acts as a passive structural scaffold. Host blood vessels and bone cells attach to this scaffold, creeping across the matrix to form new tissue. All four major graft types provide osteoconduction, making it the primary healing mechanism for synthetic and animal-derived grafts.

Experience World-Class Smile Transformations in Turkey
Now everyone can achieve a stunning Hollywood smile in Turkey with top-tier international quality and affordable prices. Our premium packages cover full clinical care, luxury hotel accommodation, private transfers, and dedicated language translation for a seamless treatment journey.
| Treatment Type | USA / UK Price Range | Turkey Package Price |
|---|---|---|
| Hollywood Smile Makeover | €10,000 – €20,000 | €1,999 – €3,499 |
| All-on-4 Dental Implants | €14,000 – €25,000 | €4,999 – €5,499 |
| Dentist Consultation | €150 – €300 | FREE |
Socket Preservation: Stopping Bone Collapse After Extraction
When a tooth is extracted, the socket undergoes rapid physiological remodeling. Without internal support, surrounding socket walls collapse, causing horizontal bone loss within six months. Socket preservation involves placing graft material into the fresh socket immediately following extraction.
By sealing the graft with a protective collagen membrane, clinicians preserve existing ridge dimensions. This straightforward procedure avoids costly full-scale ridge reconstruction later when placing dental implants.
Sinus Lift Augmentation: Expanding Upper Posterior Jaw Density
The posterior upper jaw poses anatomical challenges due to maxillary sinus pneumatization. When back teeth are missing, the sinus floor expands downward while the jaw ridge resorbs upward, leaving minimal bone for implant anchoring.
A sinus lift delicately raises the sinus membrane, placing bone graft material into the created cavity. Depending on bone height, surgeons use lateral or crestal techniques. For extensive missing teeth cases, patients can review all-on-4 dental implants to evaluate angled implant options that sometimes avoid sinus surgery altogether.
Block Bone Grafting: Solutions for Severe Defect Structural Volume
When an edentulous area suffers severe horizontal and vertical bone loss, particulate graft powders lack the structural strength to hold space against soft tissue pressure. In these situations, block bone grafting becomes necessary.
A solid block of autogenous or donor bone is contoured to fit the defect and secured using small micro-screws. Over four to eight months, host blood vessels revascularize the block, fusing it to native bone before implant placement.
Guided Bone Regeneration: The Essential Barrier Membrane Role
Grafting success relies heavily on cell exclusion principles. Soft mucosal tissue cells proliferate rapidly compared to slow-growing bone cells. If soft tissue invades the graft site, it forms non-structural fibrous tissue rather than solid bone.
Guided Bone Regeneration utilizes barrier membranes over the graft. Resorbable collagen membranes dissolve naturally over weeks, while non-resorbable membranes offer enhanced rigidity for large defects. Membranes keep soft tissue out, allowing bone cells to fill the scaffold undisturbed.
Healing Timelines Across Different Graft Materials
Healing duration varies significantly based on graft selection, systemic health, and localized blood supply. Maturation timelines include autografts taking 3 to 5 months, allografts taking 4 to 6 months, and xenografts or synthetics requiring 6 to 9 months.
Surgical Risks, Complications, and Graft Failure Drivers
Bone grafting carries overall success rates between 90% and 98% in healthy individuals. However, complications occur. The leading cause of graft failure is early membrane exposure, which allows bacteria to enter and infect the graft site.
Other risk factors include inadequate wound closure, excessive pressure from temporary dentures, graft micro-movement, and smoking. Nicotine severely constricts localized capillaries, starving the graft of oxygen and vital nutrients necessary for revascularization.
Evaluating Financial Value in Bone Augmentation Choice
Financial costs vary depending on graft source and complexity. Autografts incur higher fees due to operating times and secondary surgical care. Allografts and xenografts carry moderate material costs while eliminating secondary donor surgery.
Synthetic materials generally offer lower material expenses, though their application is limited to minor localized defects. Choosing graft materials solely based on price without assessing defect requirements increases risk of failure. For full reconstruction options, examine full dental implants cost in Turkey 2026.

Defect Architecture: Impact on Material Selection
Defect geometry directly dictates material selection. Wall-contained defects, like closed extraction sockets, retain graft particles easily, making xenografts or synthetics effective. Non-contained horizontal or vertical defects require rigid blocks or composite grafts paired with titanium-reinforced membranes.
Systemic Health Factors: Diabetic and Smoker Outcomes
Patient health significantly influences graft integration. Uncontrolled diabetes delays capillary growth, increasing infection risk. Heavy smoking restricts mucosal blood flow, doubling graft failure rates. In compromised patients, clinicians prioritize minimally invasive, highly vascularizing techniques.
Ethical and Religious Material Preferences
Material origin matters to many patients. Those abstaining from animal products may decline bovine or porcine xenografts. Similarly, some patients decline human donor allografts due to personal beliefs. In these situations, synthetic alloplasts or autografts provide effective alternatives.
Post-Operative Management: Protocols for Optimal Integration
Proper post-operative care directly impacts graft survival. Patients must avoid touching or applying pressure to the surgical site, refrain from rinsing forcefully during early healing, take prescribed antibiotics diligently, and stick to soft foods. Protecting the graft from micro-movement ensures uninterrupted blood vessel growth.
Future Developments in Bone Regeneration Science
Regenerative implantology continues to evolve rapidly. Platelet-Rich Fibrin, drawn from the patient’s blood, concentrates growth factors that accelerate soft tissue healing and graft integration when blended with particulate bone materials.
Furthermore, 3D-bioprinted custom scaffolds and recombinant human growth proteins are transforming complex bone reconstructions, minimizing surgical trauma while achieving predictable bone density for lifelong implant support.


